

My takeaway: dry needling may change pain processing, but that does not prove lasting pain relief. I would judge treatment by changes in your pain and daily activities, not by lab results alone.
Here’s how I read the findings:
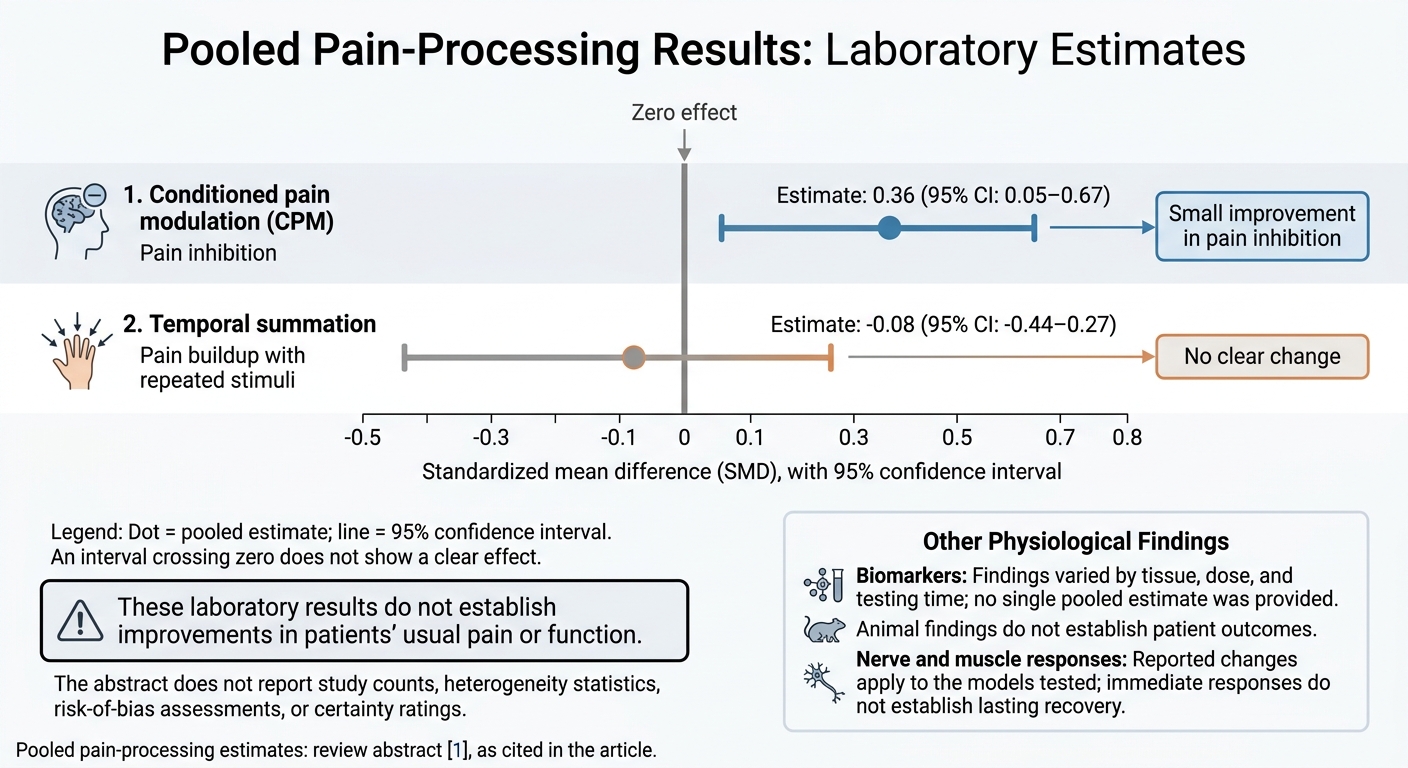
- Pain inhibition improved slightly: the pooled effect was 0.36, with a 95% confidence interval of 0.05–0.67.
- Pain buildup with repeated stimuli showed no clear change: the pooled effect was −0.08, with a 95% confidence interval of −0.44–0.27.
- Biomarker and nerve-response findings varied: results depended on the tissue, dose, and testing time. Animal findings do not establish patient outcomes for specific conditions.
- Confidence remains limited: the abstract leaves out study counts, bias assessments, and certainty ratings.
For a treatment trial, I would set goals and a reassessment date with your clinician. Track pain, movement, sleep, and one difficult daily task. Safety matters, too: soreness, bruising, and minor bleeding can occur. Sudden chest pain or shortness of breath after needling near the chest or upper back needs urgent medical assessment.
How the Review Selected and Assessed Studies
Search Methods and Study Criteria
The review included human and animal studies of biomarker outcomes. However, the abstract does not report the databases searched, search cutoff, study count, eligibility criteria, or needling protocol.[1] It also leaves out details about comparison groups, doses, body regions, and timing. These gaps limit how precisely readers can interpret the pooled results.
Combining Results and Rating Certainty
The review used random effects meta-analysis and standardized mean differences (SMDs) to put results from different scales on the same metric.[1] A 95% confidence interval shows the range of effects compatible with the data and model. If that interval crosses zero, the result does not show a clear effect.
Pooling makes sense only when studies are reasonably comparable in their outcomes, populations, techniques, doses, comparators, and follow up timing. Otherwise, results should be described separately. Because measures and timing differed across studies, the review assessed each outcome domain separately.[1]
The abstract does not name the risk of bias tool or report heterogeneity statistics or certainty ratings. Statistical significance alone cannot establish risk of bias or certainty. The table below separates what the abstract reported from what it left out for each outcome domain.
Study Methods and Results at a Glance
“Not reported” means the information was not stated in the abstract. The abstract provides no certainty ratings, and whether biomarker results were pooled needs to be checked in the full text.[1] The next section therefore presents effects by outcome domain, rather than as one combined result.
| Outcome domain | Measurement method | Study population | Comparator | Follow-up | Pooled effect | Certainty |
|---|---|---|---|---|---|---|
| Pain-related biomarkers | Molecular, inflammatory, and neurochemical assays | Human and animal studies | Comparator not specified | Timing not specified | Increases and decreases reported; no single pooled estimate provided[1] | Not reported |
| Conditioned pain modulation | Pain-conditioning and test-stimulus paradigm | Human studies; population not specified | Comparator not specified | Timing not specified | SMD 0.36; 95% CI, 0.05–0.67[1] | Not reported |
| Temporal summation | Repeated-stimulus pain response assessing pain amplification | Human studies; population not specified | Comparator not specified | Timing not specified | SMD −0.08; 95% CI, −0.44–0.27[1] | Not reported |
sbb-itb-ed556b0
Findings by Physiological Outcome
Dry Needling: Pain Processing Effects Explained
Conditioned Pain Modulation and Temporal Summation
In human pain processing tests, conditioned pain modulation (CPM) showed a small improvement in pain inhibition: SMD 0.36 (95% CI, 0.05 to 0.67). Temporal summation showed no clear change: SMD −0.08 (95% CI, −0.44 to 0.27).[1] These laboratory results do not establish improvements in patients’ usual pain or function.
Pain Related Biomarkers
Earlier literature reports immediate decreases in CGRP, substance P, cytokines, and interleukins in trigger point extracellular fluid after needle insertion.[4] Local biomarker changes do not prove pain relief. They offer clues about how needling may work, rather than measuring clinical outcomes. These findings also do not reflect every study in the review. The table separates human, animal, and pain processing results.
| Domain and model | Tissue or test; timing | Direction of effect | Pooled estimate (95% CI) | Consistency and certainty |
|---|---|---|---|---|
| Pain processing: human | Conditioned pain modulation; site and timing not specified | Small improvement[1] | SMD 0.36 (0.05 to 0.67) | Heterogeneity and certainty not reported |
| Pain processing: human | Temporal summation; site and timing not specified | No clear change[1] | SMD −0.08 (−0.44 to 0.27) | Heterogeneity and certainty not reported |
| Biomarkers: human | Trigger-point extracellular fluid; immediate | Local CGRP, substance P, cytokines, and interleukins decreased in cited literature[4] | Not available | Consistency not established; certainty not reported |
| Biomarkers: rabbit | Biceps femoris, serum, and dorsal root ganglion; immediate and 5 days | Lower-dose needling increased β-endorphin and reduced substance P; higher-dose needling increased inflammatory and angiogenic markers, with some elevations lasting 5 days[6] | Not available | Dose-dependent findings; certainty not reported |
| Autonomic response: human | Skin conductance in chronic nonspecific neck pain; immediate | Increased compared with sham needling[5] | Not available | Single study described; certainty not reported |
Nerve Excitability and Muscle Responses
Some studies measured local neuromuscular activity, though their findings applied only to the models tested. Trigger point studies reported decreases in end plate noise, end plate spikes, acetylcholine levels, and neuromuscular junction responses after needling.[7]
In the human neck pain study, skin conductance increased while local mechanical hyperalgesia decreased. Central pain processing did not change.[5] These immediate changes do not establish lasting recovery.
Clinical Meaning, Study Limits, and Safety
What the Findings Mean for Pain and Recovery
Results vary by diagnosis, comparison group, added treatments, and follow up period. In a sham controlled neck-pain trial, real and sham dry needling produced no differences in outcomes when added to multimodal care. Follow up extended to 1 year.[10]
For patients in Oklahoma City, agree on measurable goals before treatment. Track pain, mobility, and one daily activity that’s difficult to do. Also track sleep and medication use, and set a date to reassess. Use those outcomes to judge progress.
Evidence Strengths and Limits
Different tests measure different things. Biomarkers measure molecular activity, while pain processing tests assess sensory responses. Electrical recordings measure nerve or muscle activity, and muscle tests assess performance. These distinctions matter when interpreting the biomarker, pain processing, and nerve-response findings above and the pooled lab findings below.
| Evidence strength | Corresponding limitation | What it means for interpretation |
|---|---|---|
| Small pooled effects | The average change may be modest and may not meet a patient’s threshold for meaningful improvement | Statistical significance does not guarantee noticeable improvement |
| Varied protocols and tissues | Needle depth, muscles, dose, technique, and diagnosis may differ | Findings may not apply to every condition or treatment approach |
| Different comparison groups | Studies may compare dry needling with sham, usual care, exercise, or no treatment | The apparent effect depends on the comparison |
| Different measurement tools and outcomes | A physiological signal may change without a meaningful patient benefit | A test result alone does not prove clinical benefit |
| Different testing times | Immediate, short term, and delayed measurements may show different effects | An early response does not establish a lasting effect |
| Short follow up | Many studies do not establish long term pain or functional outcomes[12] | Claims about lasting relief remain uncertain |
| Animal to human translation | Animal biomarker changes may not reflect human symptoms or disability | Mechanistic findings need confirmation in well designed human trials |
Safety and Treatment Decisions
Temporary soreness, bruising, and minor bleeding can occur. Serious complications are uncommon but have been reported, including pneumothorax a collapsed lung and infection.[3][9][11] Seek urgent medical assessment for sudden chest pain or shortness of breath after needling near the chest or upper back.
Before treatment, tell your clinician about medications, bleeding problems, immune compromise, skin infections, pregnancy, and other relevant conditions. Do not stop blood thinning medication on your own. Any change requires guidance from the prescribing clinician.[8][9]
Ask your clinician about practitioner qualifications, anatomy training, infection control procedures, informed consent, and how they handle new or worsening symptoms. Clarify costs, insurance coverage, and out of pocket expenses. Agree on when to reassess. If daily function isn’t improving or adverse effects persist, review the plan.
Conclusion: What the Evidence Supports
The pooled findings suggest a small CPM effect and no clear change in temporal summation.[1] Effect size, consistency, and certainty are separate questions. Changes in pain processing pathways don’t establish that a treatment produces meaningful or lasting clinical gains.
Research Needed to Link Mechanisms With Recovery
Studies need standardized needling protocols, co-interventions, and outcome timing, along with adequate sample sizes, preregistered mechanistic outcomes, sound comparison groups, and longer follow-up. Researchers should test whether changes in CPM, biomarkers, nerve excitability, or muscle responses predict better function, sleep, and quality of life.
What Patients Can Discuss
Talk with your clinician about whether a time limited trial fits your health history, preferences, goals, and budget and how it would work alongside exercise or other care. Judge the trial by changes in daily function, not by its proposed mechanism alone.
FAQs
Can these findings predict whether dry needling will help me?
Dry needling may help with musculoskeletal pain linked to muscle trigger points. Studies found short-term improvements in pain and function compared with sham treatment. In a randomized trial for greater trochanteric pain syndrome, dry needling worked about as well as cortisone over 6 weeks.
Results vary by condition, and treatment usually takes multiple sessions. These findings don’t guarantee that dry needling will help you [1][2].
How much improvement would make dry needling worthwhile?
Whether dry needling is worth it depends on your health goals and how much it improves your pain and physical function [1]. Clinical trials, for example, reported average pain scores falling from 5.4 to 2.8 on a 10-point scale over six weeks, along with gains in function [2].
Results vary. To judge your progress, look at how well you can return to daily activities and meet your functional goals [2][1].
How long should I try dry needling before reassessing?
The number of sessions depends on your condition. Subacute conditions typically respond well within two to three sessions, while chronic pain or persistent trigger points may need five to six. Patients receive an average of about 5.4 treatments.
Your response may differ, so work with your practitioner to build a plan that fits your needs. If you’re not seeing improvement, ask your clinician to review your progress and decide whether to adjust your treatment plan.

Comments are closed